
Types of myeloma
 Fact-checked by
The rare blood cancer myeloma has several different types, each with its own characteristics and prognosis. Identifying a person’s myeloma type at diagnosis helps doctors choose the right treatment plan.
Diagnosis and classification
Myeloma is a cancer that develops from plasma cells — a type of white blood cell that makes antibodies to help fight infections. Genetic changes cause these plasma cells to grow out of control in the bone marrow, the spongy tissue inside bones where blood cells are made. The cells often produce an abnormal protein called M protein.
After a diagnosis, doctors run additional tests to determine the type of myeloma a person has. Doctors consider several factors when classifying myeloma, including:
- whether there are signs and symptoms of organ damage
- the type of M protein produced by the abnormal plasma cells
- the location of the cancerous cells in the body
- the specific genetic characteristics of the cancer cells
Accurate myeloma classification helps doctors choose the right monitoring and treatment plan for the best possible outcomes.
Multiple myeloma
Multiple myeloma occurs when myeloma cells are found in multiple areas of the bone marrow at the same time. These cells crowd out healthy blood cells and usually produce large amounts of identical M proteins, also called monoclonal proteins.
Smoldering multiple myeloma
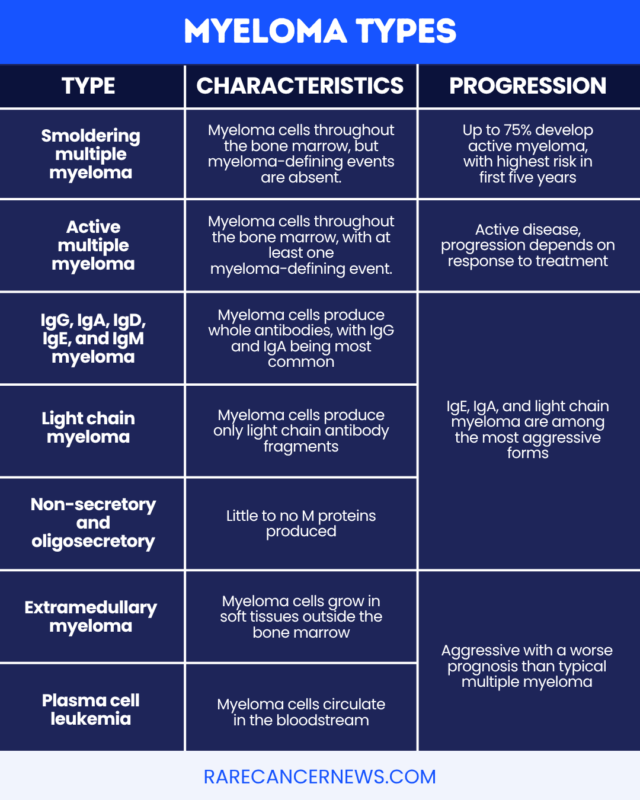
Smoldering multiple myeloma (SMM) is an early precancerous stage in which tests may find M protein in the blood or urine and/or abnormal plasma cells in the bone marrow. However, there are no myeloma-defining events. This means there are no clinical signs or symptoms of myeloma, or test findings that suggest a high risk of progressing to active myeloma in the near future.
SMM is technically not cancer and is generally not treated unless a person is at high risk of progressing to active, symptomatic myeloma. However, around 50% of people with SMM develop active myeloma within the first five years. This makes careful monitoring important.
Active multiple myeloma
In people with myeloma, active disease is marked by at least one myeloma-defining event. These include signs of organ damage caused by myeloma cells and the abnormal proteins they produce, or test findings that indicate a high risk of such damage developing in the near future. These events may include:
- bone lesions (areas of bone damage) found on imaging scans
- high blood calcium levels
- poor kidney function
- anemia, or too few red blood cells
- cancerous plasma cells making up at least 60% of the cells in the bone marrow
- a highly abnormal ratio of antibody fragments called free light chains in the blood
- at least two focal lesions on an MRI scan, each measuring at least 5 mm
Although symptoms are not required for a diagnosis, most people with active myeloma have symptoms. This is why it is also called symptomatic myeloma. A diagnosis of active multiple myeloma typically warrants immediate treatment. Although active myeloma cannot currently be cured, treatment may help control the disease, ease symptoms, prevent further organ damage, and improve quality of life.
Other myeloma classifications
Myeloma can also be classified by the type of M protein produced by myeloma cells and where the cancerous plasma cells are found in the body. These myeloma classifications help doctors assess a person’s prognosis and plan treatment.
Myeloma by antibody type
Multiple myeloma has several subtypes based on the type of abnormal antibody, or M protein, produced by the cancer cells.
Antibodies, also called immunoglobulins (Ig), are Y-shaped proteins made up of two long parts (heavy chains) and two shorter parts (light chains). There are five heavy chain types — IgG, IgA, IgD, IgE, and IgM — and two light chain types, kappa and lambda.
These heavy and light chains can occur in different combinations, but a person’s myeloma cells typically produce only one type:
- IgG myeloma is the most common form, occurring in more than half of people with multiple myeloma
- IgA myeloma is the second most common form, and is sometimes linked to a worse prognosis than IgG myeloma
- IgD, IgE, and IgM myeloma are all rare, and other plasma cell conditions can involve these same antibody types
For most people with myeloma, cancer cells produce one of the above types of fully intact antibodies. But in other cases, myeloma cells produce only part of an antibody or little to no M protein:
- Light chain myeloma: myeloma cells produce only the light chain part of the antibody — either kappa or lambda
- Non-secretory or oligosecretory myeloma: little to no M protein is detected in the blood or urine
Light chain myeloma
Light chain myeloma, also called Bence Jones myeloma, accounts for about 15% of myeloma cases. It is associated with a significantly higher rate of kidney impairment and worse survival than IgA or IgG myeloma.
Non-secretory and oligosecretory myeloma
Traditionally, non-secretory myeloma has been used to describe about 1%-3% of myeloma cases in which standard tests detect little or no M protein. This may be because myeloma cells produce little or none of the protein or do not release it. Today, cases in which small amounts of M protein can be detected with more sensitive tests are sometimes called oligosecretory myeloma. Both can lead to the same types of organ damage as other forms of myeloma, but may require different ways of monitoring the disease because standard blood and urine tests are less reliable.
Myeloma by anatomical location
Multiple myeloma is typically found in multiple locations throughout the bone marrow. In rare cases, myeloma cells can also be found in the bloodstream or other tissues. These forms of the cancer tend to be more aggressive and harder to treat.
- Extramedullary myeloma: myeloma cells form tumors (plasmacytomas) in tissues and organs outside the bone marrow
- Plasma cell leukemia: myeloma cells circulate in the bloodstream
Both are rare forms of myeloma that are generally more aggressive and have a worse prognosis than myeloma limited to the bone marrow. They can be present at diagnosis or develop later as the disease progresses.
Clinical staging systems vs. myeloma types
After a diagnosis, patients may hear doctors talk about both their myeloma type and stage. These terms describe different features of the blood cancer:
- Myeloma type: describes the type of abnormal protein produced by the cancer cells and whether the cancer is limited to the bone marrow
- Myeloma stage: helps estimate a patient’s prognosis based on genetic characteristics of the cancer cells and other laboratory measures
Genetic features may also help classify myeloma subtypes, but they play a key role in determining stage and prognosis. Doctors use both myeloma type and stage to develop an individualized treatment and monitoring plan.
Comparing myeloma subtypes: Prognosis and characteristics
While each of these myeloma types originates from abnormal plasma cells, they have distinct characteristics that influence their prognosis.
In general, smoldering myeloma is a milder form of the disease, without any symptoms or evidence of cancer-related damage in the body. Among the subtypes of active multiple myeloma, those associated with a more aggressive disease course include:
- myeloma associated with IgE, IgA, and light chain antibody types
- myeloma that has spread out of the bone marrow
The symptoms of different myeloma types are generally similar, but may vary in severity. All forms of active myeloma require treatment, but different approaches may be used depending on the aggressiveness of the cancer.
Precancerous and related plasma cell disorders
Myeloma is also related to other conditions that involve abnormal plasma cells or other immune cells, but are distinct diseases. In some cases, these conditions can become multiple myeloma later on. They include:
- Monoclonal gammopathy of undetermined significance (MGUS): a precancerous condition in which a small number of abnormal plasma cells and M protein can be detected, but there are no signs of myeloma-related organ damage.
- Solitary plasmacytoma: a plasma cell cancer where myeloma cells form a solitary tumor in a single location, rather than being found in multiple areas throughout the bone marrow.
Monoclonal gammopathy of undetermined significance
About 1% of people with MGUS develop myeloma or another blood cancer each year. MGUS rarely causes symptoms and is typically not treated, but requires careful monitoring for progression to active myeloma.
Solitary plasmacytoma
Plasmacytomas can form in the bone, where they mainly cause bone pain without other signs of myeloma-related organ damage, or in soft tissues outside of the bone (extramedullary), with symptoms that vary by location. This condition is often treated with radiation therapy and has a good prognosis if it does not progress to multiple myeloma. However, around 70% of people with solitary plasmacytoma of the bone go on to develop multiple myeloma.
Rare Cancer News is strictly a news and information website about the disease. It does not provide medical advice, diagnosis, or treatment. This content is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website.


