
Prognosis of myeloma
 Fact-checked by
A prognosis in myeloma varies depending on a wide range of factors, including overall health, cancer stage, and each individual’s response to treatment. There is no simple way to predict how long a person with the rare blood cancer will live, but doctors use staging systems to estimate long-term outlook and make informed treatment decisions.
In myeloma, often called multiple myeloma, cells in the spongy tissue inside some bones, called bone marrow, become cancerous and grow out of control. The major goal of treatment is to achieve and maintain remission, when signs and symptoms of active cancer are low or absent. However, relapses, when the cancer returns or progresses after remission, are common.
While myeloma is generally considered incurable, modern treatment options are improving the outlook, and some people can maintain remission for long periods of time. Because of that, experts are working to define what a cure might mean for myeloma.
Prognostic indicators
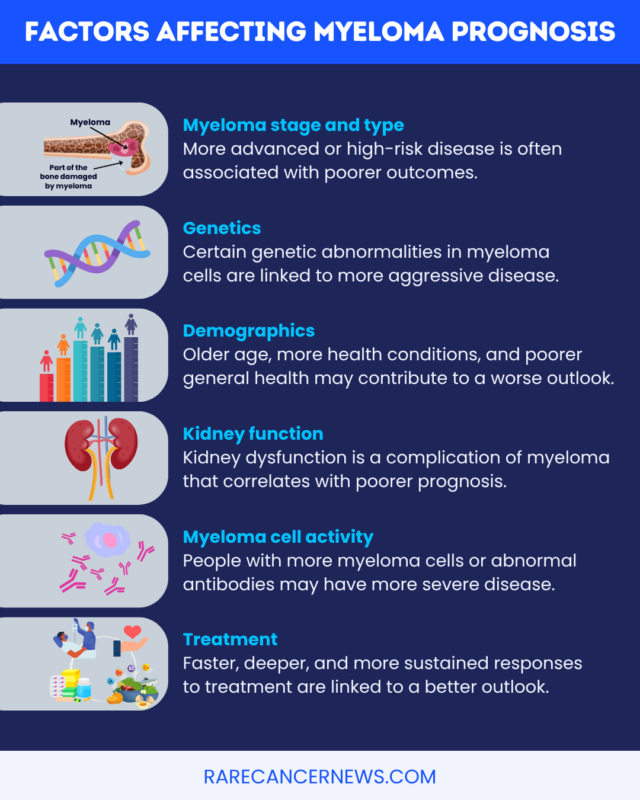
Many factors can affect myeloma life expectancy and prognosis, including:
- the myeloma type and stage
- the genetic characteristics of the cancer cells
- the patient’s age, general health, and other medical conditions
- kidney function
- the amount of myeloma in the body — including myeloma cells and the abnormal proteins they produce — and how quickly this changes
- the type of treatment and how well the myeloma responds to it
Certain genetic abnormalities in myeloma cells are associated with a more aggressive disease course and a higher risk of poor outcomes. Likewise, a greater degree of kidney damage, a common complication of myeloma, is linked to a worse prognosis. Myeloma that is growing quickly or has spread outside of the bone marrow is also a sign of a more aggressive disease course.
Older people and those with more coexisting health problems may also have a harder time tolerating aggressive treatments and have a worse overall outlook.
Treatment responses are a major prognostic indicator. Individuals who respond to initial treatment and stay in remission for longer generally have a better long-term outlook than people who fail to respond to initial treatment — said to have refractory disease or those who quickly relapse.
Doctors use various laboratory and clinical tests to measure these prognostic factors. A number of them are incorporated into standard myeloma staging systems, which help predict disease progression and risk.
Myeloma staging
Standard tumor staging systems don’t translate easily to blood cancers, including multiple myeloma. Instead, specific myeloma staging criteria are used to inform a person’s long-term outlook. There are two main staging systems used for people with myeloma:
- International Staging System (ISS) and revised ISS (R-ISS): These use laboratory measures to classify patients into three risk stages that predict prognosis and survival.
- Durie-Salmon Staging System: This system uses laboratory and clinical indicators of cancer-related tissue damage to estimate how much myeloma has accumulated in the body.
Still, while disease staging is used to guide clinical decision-making, it is not an absolute determinant of a person’s long-term prognosis. That long-term outlook may be influenced by factors such as treatment responses and overall health.
These systems are used to predict outcomes for people with active myeloma. Among people with smoldering myeloma — a precancerous condition where some myeloma cells are present but they aren’t causing symptoms — about 50% of patients will progress to active myeloma in the first five years after diagnosis.
International staging system
The ISS, developed in 2005, estimated a person’s prognosis based on two laboratory measures. The R-ISS, a 2015 revision, added additional prognostic markers and is now the most commonly used version. Specifically, it considers:
- serum beta-2-microglobulin (B2M): a protein that circulates in the blood and urine, and in which elevations can indicate poor kidney function and disease activity
- serum albumin: a protein made by the liver, low levels of which can signal kidney problems and inflammation
- lactate dehydrogenase (LDH): an enzyme found throughout the body, in which elevations can reflect more aggressive disease
- chromosomal (cytogenetic) variations: abnormalities in the chromosomes, the cellular structures that store DNA, in myeloma cells can be associated with more aggressive disease, as can certain high-risk changes
B2M, albumin, and LDH are measured in the blood. Cytogenetic abnormalities are usually detected by analyzing a sample of cancer cells from the bone marrow, using a specialized technique called fluorescence in situ hybridization, or FISH.
Based on the results of these tests, the R-ISS defines three disease stages. Stage 1 is generally associated with the best prognosis, and Stage 3 with the worst.
Scroll horizontally to view all columns -->
| R-ISS Stage | Criteria |
|---|---|
| Stage 1 | All of the following: • serum B2M below 3.5 mg/L • serum albumin of at least 3.5 g per deciliter (dL) • no high-risk cytogenetic abnormalities • normal LDH |
| Stage 2 | Not R-ISS stage 1 or 3 |
| Stage 3 | Serum B2M of at least 5.5 mg/L and either:
• high-risk cytogenetic abnormalities |
The original ISS considered only B2M and albumin. A newer set of criteria, created after the R-ISS and called the second revision of the ISS (R2-ISS), has been developed, although it is not yet as widely used.
In 2025, experts developed a set of criteria to define high-risk myeloma, which may be used alongside the R-ISS system. On average, a high-risk myeloma prognosis involves a greater risk of progression and death compared with standard-risk disease.
Durie-Salmon staging system
The Durie-Salmon system dates to 1975, but has evolved as modern testing techniques have become available. Durie-Salmon staging is based on tests that evaluate the degree to which myeloma is affecting the body, including:
- levels of the protein hemoglobin, a deficiency in which reflects a lack of healthy red blood cells (anemia) due to the overgrowth of myeloma cells
- blood calcium, which is elevated with myeloma-related bone damage
- bone lesions, or areas of damage visible on imaging tests
- production rates of M-protein, the abnormal antibodies produced by myeloma cells that cause tissue damage
- urine levels of M-protein antibody fragments called light chains
Based on these factors, the system estimates the number of myeloma cells that are present and places patients into one of three stages:
Scroll horizontally to view all columns -->
| Durie-Salmon Stage | Criteria |
|---|---|
| Stage 1
Low myeloma cell mass — fewer than 600 billion myeloma cells per square meter |
All of the following:
• hemoglobin levels of at least 10 g/dL |
| Stage 2
Intermediate myeloma cell mass — 600 billion to 1,200 billion myeloma cells per square meter |
Results that don’t fit with Stage 1 or Stage 3 |
| Stage 3
High myeloma cell mass — more than 1,200 billion myeloma cells per square meter |
One or more of the following:
• hemoglobin levels of less than 8.5 g/dL |
Within each stage, the Durie-Salmon system also identifies two subclasses:
- class A: normal or near-normal kidney function
- class B: abnormal kidney function
Although this classification can help determine the extent of myeloma and its effects on organs and tissues in the body, it has limitations in terms of predicting prognosis.
Measurable residual disease
Measurable residual disease (MRD), sometimes called minimal residual disease, refers to the small number of remaining myeloma cells in the body after treatment, which occurs even when remission is achieved.
MRD is detected with very sensitive laboratory techniques. Traditionally, a person is considered MRD-negative if these tests detect fewer than one abnormal myeloma cell per 100,000 cells in a bone marrow sample. Sometimes, more sensitive approaches use a cutoff of fewer than one in every million cells. In general, MRD negativity is associated with a better prognosis, including a lower risk of relapse and longer survival.
Relapsed and refractory disease
Although many people with myeloma reach remission with treatment, relapses are common, and some people may fail to respond adequately to treatment in the first place — when their cancer is then called refractory myeloma.
Relapsed or refractory multiple myeloma, or RRMM, tends to be linked to a poorer prognosis and lower life expectancy. While remission periods often become shorter or more difficult to achieve with repeated relapses, newer treatment options can still produce meaningful responses for some people with RRMM, and outcomes vary widely.
With each new relapse that occurs, doctors may reassess a person’s myeloma stage and other prognostic factors to determine the outlook and make a new treatment plan.
Survival rates and long-term outlook
Myeloma survival rates are improving as new treatments become available. In fact, recent studies suggest that the average life expectancy after diagnosis now exceeds 10 years.
In the U.S., the five-year relative survival rate for myeloma diagnosed from 2016 through 2022 is 63.7%. This means that people with myeloma were nearly 64% as likely to be alive five years after diagnosis as people in the general population without cancer.
Survival statistics in England from 2016 to 2020 estimated that more than 55% of people with myeloma would survive their cancer for at least five years. This varied by disease stage, with better survival in Stage 1 (nearly 80%) than in Stage 2 (approximately 60%) or Stage 3 (about 40%).
These statistics may lag somewhat behind more recent treatment advances, so newer data may show these rates improving over time. Moreover, these are population-based averages, and individual survival can vary based on many factors. These include complications associated with myeloma, such as kidney failure or serious infections, as well as age-related factors and health conditions unrelated to the blood cancer.
People with myeloma should talk with their healthcare team to better understand their individual prognosis.
Rare Cancer News is strictly a news and information website about the disease. It does not provide medical advice, diagnosis, or treatment. This content is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website.


