Myeloma diagnosis: Tests and procedures
 Fact-checked by
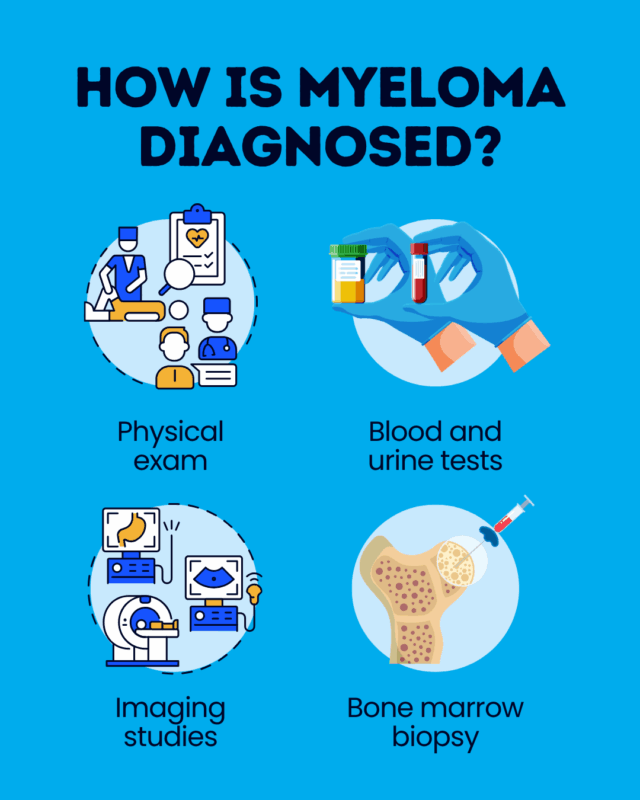
There isn’t a single test that can tell whether someone has myeloma, so doctors use the collective results of a physical exam, blood and urine tests, bone marrow examination, and imaging studies to establish a myeloma diagnosis.
Myeloma is a rare blood cancer that occurs when plasma cells — the immune cells responsible for making antibodies — grow out of control in the bone marrow, the spongy tissue inside bones where blood cells are made. Plasma cells usually make antibodies that help fight infections, but cancerous myeloma cells produce an abnormal antibody called M protein, which can cause severe damage to vital organs and tissues.
After myeloma is identified, part of the diagnostic process also involves staging the disease to determine how far it has spread and how it needs to be treated.
Importance of early diagnosis
The more advanced myeloma is by the time it is diagnosed, the harder it is to treat. Not only will there be more cancer cells to eliminate, but these cells may have acquired new genetic mutations that help them survive. An early diagnosis gives a person more treatment options and the best chance of a good response.
Delayed diagnosis can also result in a higher symptom burden and a greater risk of organ damage or other serious complications. Timely detection allows for a prompt start of myeloma treatments that can limit these problems. While myeloma is generally considered incurable, treatment can extend survival and make living with the disease easier.
Still, it can be difficult to diagnose myeloma because the disease often does not cause symptoms in its early stages, so understanding when to seek clinical evaluation is critical for ensuring the best possible long-term outcomes.
Initial clinical evaluation
In some cases, myeloma may be asymptomatic, and the first signs may be detected on blood tests done for other reasons. In other cases, a person may be experiencing symptoms that bring them to the doctor or to the emergency department.
The first step in the diagnostic process is usually exploring medical history and performing a physical exam. Common findings physicians use to identify active, symptomatic myeloma may be summarized under the acronym CRAB:
- Calcium elevations in the blood (hypercalcemia), with symptoms of extreme thirst, appetite loss or nausea, constipation, or confusion
- Renal (kidney) dysfunction, with symptoms like infrequent urination or leg swelling
- Anemia, or a lack of healthy red blood cells, leading to fatigue or weakness
- Bone problems, including pain, fractures, or weakness
Other possible signs of myeloma may include frequent infections or easy bruising and bleeding.
Diagnostic tests and procedures
If myeloma is suspected, several other tests will be run to establish whether the cancer is present and, if so, what type it is and how advanced it is. Diagnostic tests for myeloma may include:
- blood and urine tests
- bone marrow analyses
- imaging studies
Blood and urine tests
Some of the most important lab tests that may be run to help diagnose myeloma include:
- tests to detect M protein and other antibodies in blood or urine
- complete blood count, to measure levels of healthy blood cells
Elevated M protein in blood and urine is characteristic of myeloma. The balance of other antibody types, including antibody fragments called kappa and lambda free light chains, is also often altered.
Because myeloma cells crowd out healthy blood cells in the bone marrow, levels of red blood cells, white blood cells, and platelets may be lower than normal in a person with myeloma.
Other blood tests may also be used to look for other classic CRAB features, including increased calcium levels and kidney insufficiency.
Myeloma blood tests may also be used to look for signs of kidney dysfunction and check calcium levels and levels of proteins linked to disease prognosis that are used for disease staging, including albumin, lactic dehydrogenase (LDH), and beta-2 microglobulin (B2M).
Bone marrow test
A bone marrow test involves inserting a thin, hollow needle into a bone and extracting a sample for analysis under a microscope. This test usually includes:
- bone marrow aspiration, to remove a liquid marrow sample
- bone marrow biopsy, to collect a small piece of solid bone marrow tissue
The samples, which are usually taken from the hip bone, then go to a lab for testing. A specialist will examine the size, shape, and appearance of cells in the collected sample to determine the presence and abundance of cancerous cells.
Myeloma cells are also analyzed using several laboratory techniques to identify underlying genetic abnormalities that cause plasma cells to grow out of control. The specific types of genetic alterations found in these cells will influence disease staging and prognosis.
Imaging
Imaging tests are a key part of diagnosing myeloma and determining how much it has spread. They may include:
- Positron emission tomography-CT scans: use a radioactive tracer to detect areas of increased metabolic activity associated with myeloma
- Low-dose, whole body CT scans: create a detailed picture of the bones and detect areas of of bone damage
- MRI scans: done in certain cases to visualize potential signs of myeloma-related bone damage
How is myeloma diagnosed?
A diagnosis of active multiple myeloma used to require the presence of at least one CRAB clinical feature, but more recent guidelines — sometimes called the SLiM CRAB criteria — also allow a diagnosis to be made if laboratory features strongly suggest the disease will progress to active myeloma.
Current myeloma diagnostic criteria require that at least 10% of the bone marrow be made up of cancerous plasma cells or that a biopsy-proven plasma cell tumor (plasmacytoma) is present, in addition to at least one of the following:
- hypercalcemia
- kidney impairment
- anemia
- at least one region with signs of bone destruction on imaging scans
- bone marrow tests showing that at least 60% of the bone marrow is made up of cancerous plasma cells
- at least a 100-fold difference in blood levels of kappa and lambda free light chains in people with absolute light chain levels of at least 100mg/L
- more than one cluster of plasma cells in the bone marrow on MRI scans, each measuring at least 5 mm
If abnormal plasma cells or M protein are somewhat elevated but the diagnostic criteria are not met, a person may be diagnosed with one of two precancerous conditions that commonly precede myeloma, called monoclonal gammopathy of undetermined significance (MGUS) or smoldering myeloma.
These conditions may or may not progress to active myeloma, so people diagnosed with them need to be carefully monitored.
Myeloma staging
Once myeloma has been identified, doctors will stage the disease, that is, determine where it has spread and how quickly it is growing. This facilitates treatment planning.
There are various myeloma staging systems that may be used, but the one that’s usually favored is the Revised International Staging System, which considers four factors known to influence disease prognosis:
- B2M blood levels
- albumin blood levels
- LDH blood levels
- the specific genetic abnormalities found in the cancer cells
Lower albumin levels, as well as higher B2M and LDH, are associated with a worse prognosis, as are certain types of genetic abnormalities. From this, myeloma is categorized into three stages, with stage 1 being the least aggressive and stage 3 being the most aggressive.
A newer system, called the Second Revision of the International Staging System, might sometimes be used. It looks at additional genetic biomarkers and splits patients into four stages rather than three.
There are also a number of other factors that can influence a myeloma prognosis, and which a doctor may consider when deciding on a treatment plan, including age, kidney function, and overall health.
Distinguishing myeloma from other conditions
It is critical to distinguish MGUS and smoldering myeloma from active myeloma in the diagnostic process, as the monitoring and treatment approach differs. Levels of abnormal plasma cells and M protein, along with the presence or absence of clinical symptoms, help doctors make the distinction.
Scroll horizontally to view all columns -->
| MGUS | Smoldering multiple myeloma | Active multiple myeloma | |
|---|---|---|---|
| Cancerous myeloma cells in the bone marrow | less than 10% | between 10% and 60% | more than 10% |
| M protein in the blood | less than 3 g/dL | 3 g/dL or more | 3 g/dL or more |
| Symptoms of organ damage or other myeloma-defining events | no | no | yes |
Myeloma may also overlap with other plasma cell disorders:
- solitary plasmacytoma
- AL (light chain) amyloidosis, a condition where abnormal light chains produced from plasma cells build up and damage tissues
- Waldenström macroglobulinemia, a cancer that’s characterized by overproduction of immunoglobulin M antibodies
Each of these conditions is treated differently, so it is important to get the right diagnosis. Physicians can usually home in on this by looking for the specific pattern of abnormal antibodies, protein buildup, organ damage, and related symptoms that characterize each disorder.
Rare Cancer News is strictly a news and information website about the disease. It does not provide medical advice, diagnosis, or treatment. This content is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website.